Epigenetic Clocks Explained: What DNA Methylation Can and Cannot Say About Biological Age
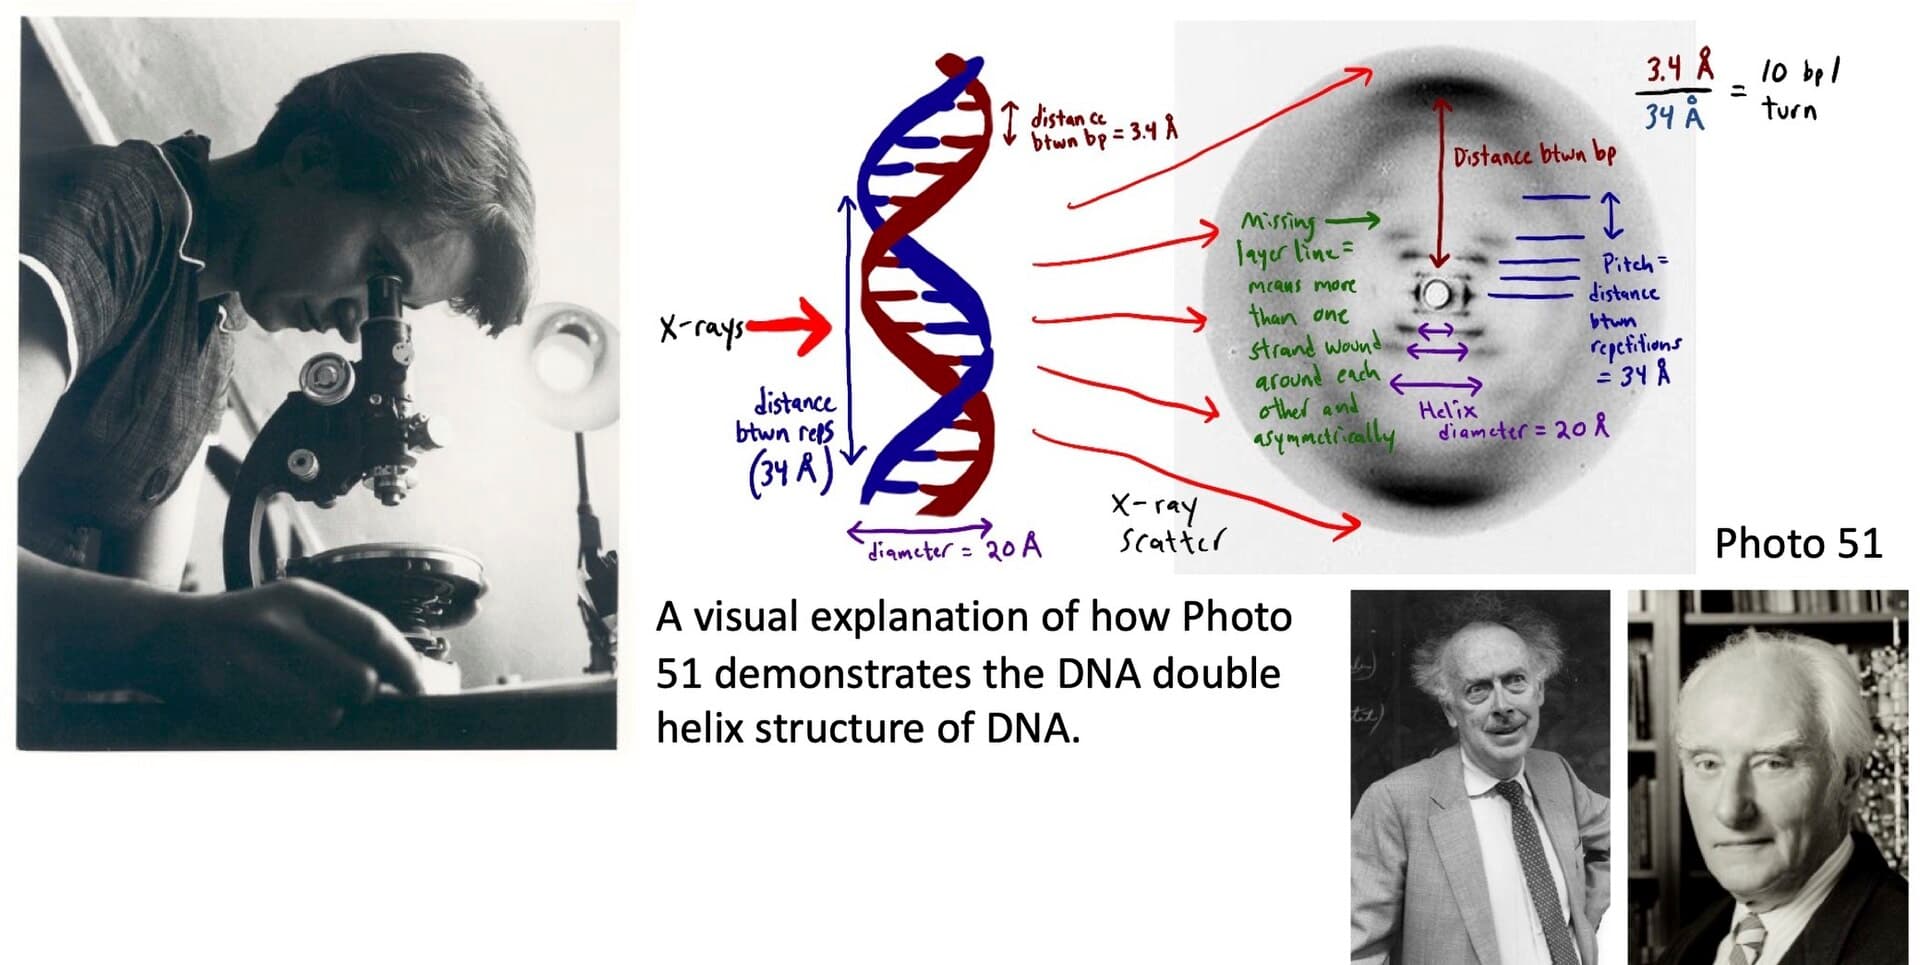
Photo: Bioanthropologist1 (CC BY 4.0) / Wikimedia Commons / CC BY 4.0
People age at different rates, and not every tissue in one body ages at the same speed. Researchers therefore look for measurements that capture something about aging beyond the number of years since birth. Epigenetic clocks are statistical models that estimate an age-related quantity from the chemical tags, mainly DNA methylation, found at selected positions along the genome.
The word "clock" suggests a precise instrument reading a single hidden biological age. The reality is closer to a family of calibrated estimators. Some were trained to guess calendar age, some to track mortality risk, and one to measure how fast a person's body is changing. Their output depends on the tissue sampled, the mix of cells in it, the laboratory method, the population used for training, and the objective the model was built to optimize.
An epigenetic-age estimate is therefore a biomarker. It is not a diagnosis and not a complete description of anyone's health. The gap between estimated and calendar age can generate a research hypothesis, but it does not prove that a person is aging faster, has a disease, or can close the gap with a particular intervention.
Direct answer: An epigenetic clock is a statistical model that uses DNA-methylation levels at a set of sites to estimate chronological age or another age-related outcome. "Age acceleration" is a model-dependent difference or residual, not a universal verdict on health. Results vary by tissue, cell composition, sample quality, clock design, population and laboratory method. Clock research illuminates aging biology, but consumer results should not be treated as diagnosis, treatment guidance, or proof that an intervention changes lifespan. 1 2 3
Medical information disclaimer: This article explains biomedical research and is not medical advice. It cannot diagnose aging, disease or risk, interpret a personal test, or recommend a supplement, treatment or lifestyle intervention. For urgent symptoms or an emergency, contact local emergency services rather than relying on an article or AI system.
What epigenetics and DNA methylation mean
Epigenetics describes molecular regulation that can influence gene activity without changing the underlying DNA sequence. The broader topic is covered in how your environment changes the way your DNA is read. DNA methylation is the best-studied mechanism: enzymes attach a methyl group (a carbon atom with three hydrogens) to cytosine, one of the four DNA letters. In human cells this happens mostly where a cytosine sits directly before a guanine, a pairing called a CpG site.
Think of the genome as a very long cookbook and methylation as the sticky notes placed on certain recipes. The recipe text stays the same, but the notes influence which pages the cell tends to open. A methylation mark is not a simple on/off switch, though. Its effect depends on where it lies, the packaging of DNA around it (chromatin), the proteins that bind nearby, and the cell type.
That context dependence is why a clock never reads one "age gene." It combines small signals from hundreds of sites, each of which nudges the estimate a little up or a little down, much as a bathroom scale averages the pressure from many load cells.
How methylation is measured
Most clock data come from DNA extracted from blood, saliva, or tissue. The DNA is treated with bisulfite, a chemical that converts unmethylated cytosines into another base while leaving methylated cytosines intact. A microarray or sequencer then reads which sites changed, and the fraction of molecules still methylated at each site becomes a number between 0 and 1.
Hannum and colleagues used the Illumina HumanMethylation450 array, which probes more than 450,000 CpG sites. 2 A clock then takes a small subset of those sites and applies learned weights to produce one figure.
How an epigenetic clock is built
Training data and target
Researchers collect methylation measurements from samples with a known label. A penalized regression method called an elastic net (a regression that automatically drops most inputs and shrinks the weights of the rest) picks the sites that best predict the label. The label might be calendar age, a composite of blood-test markers, years until death, or a longitudinal rate of decline.
Feature selection
The model may keep dozens or hundreds of sites out of hundreds of thousands. Sites that predict well in the training data can behave differently in another population or tissue, which is the standard overfitting problem in statistics.
Validation
A clock should be tested on data not used for training. Horvath's 2013 clock, for example, reported a correlation of 0.97 with age and a median error of 2.9 years in its training data, and 0.96 and 3.6 years in held-out test data, a deliberate illustration of why training performance alone flatters a model. 1 A strong correlation with calendar age does not show that the clock captures mechanisms that cause aging.
Calibration
A model trained across one age range or population may systematically under- or over-estimate in another. Good reports state the error and uncertainty. A single number without an interval can imply more precision than the assay supports.
A short history of the major clocks
The field is young. The first widely used clocks appeared in 2013, and each generation changed what the model was asked to predict.
| Clock | Year | Trained to predict | Sites and tissue | Notable detail |
|---|---|---|---|---|
| Horvath multi-tissue | 2013 | Chronological age | 353 CpGs; 51 healthy tissue and cell types | Embryonic stem cells read close to age zero 1 |
| Hannum blood clock | 2013 | Chronological age | Selected from 450,000+ sites; whole blood | 656 people aged 19 to 101 2 |
| PhenoAge | 2018 | "Phenotypic age" built from nine blood markers plus age | 513 CpGs; blood | About 4.5% higher mortality risk per extra year of clock age 3 |
| GrimAge | 2019 | Time to death | Seven protein surrogates plus smoking pack-years; blood | Outperformed older clocks for lifespan prediction in the authors' tests 4 |
| DunedinPACE | 2022 | Pace of aging over two decades | 173 CpGs; blood | Test-retest reliability ICC of 0.96 5 |
| DamAge and AdaptAge | 2024 | Causality-enriched age | Sites selected with Mendelian randomization | Separates harmful from adaptive changes 7 |
Horvath and Hannum: the chronological-age generation
Steve Horvath's 2013 paper in Genome Biology used about 8,000 samples from 82 datasets covering 51 healthy tissues and cell types. An elastic net chose 353 CpGs, 193 of which gain methylation with age and 160 of which lose it. 1 The same paper reported that embryonic stem cells have a methylation age near zero, that induced pluripotent stem cells are substantially younger than the cells they came from, and that cancer samples across 20 cancer types showed significant age acceleration. 1
The Hannum clock, published in Molecular Cell, was built from whole blood of 656 people aged 19 to 101. Predicted and actual age correlated at 0.96 in the primary cohort and 0.91 in the validation cohort, with mean errors of 3.9 and 4.9 years. 2 When the authors applied it to other tissues such as breast, kidney, lung, and skin, each needed its own linear adjustment, an early sign that blood-trained models do not transfer cleanly. 2
These first-generation clocks are best understood as very good estimators of calendar age. Their usefulness for health research comes from the residual: people whose predicted age exceeds their calendar age may differ in some way from people whose predicted age is lower.
PhenoAge and GrimAge: training on risk
Morgan Levine and colleagues took a two-step route for PhenoAge. They first defined a "phenotypic age" from chronological age and nine routine clinical markers: albumin, creatinine, glucose, C-reactive protein, lymphocyte percent, mean cell volume, red cell distribution width, alkaline phosphatase, and white blood cell count. They then trained a methylation predictor of that score, which ended up using 513 CpGs. 3 In the paper, each one-year increase in DNAm PhenoAge was associated with roughly a 4.5% higher risk of all-cause mortality after adjusting for calendar age. 3
GrimAge, from Ake Lu and colleagues, went further. It combines methylation-based estimators of seven plasma proteins (adrenomedullin, beta-2 microglobulin, cystatin C, GDF-15, leptin, PAI-1, and TIMP-1) and of smoking pack-years into a lifespan predictor. 4 In the authors' meta-analysis it outperformed Horvath, Hannum, and PhenoAge at predicting time to death, with a hazard ratio of about 1.10 per year of age acceleration, and it also predicted time to cancer and to coronary heart disease. 4
Notice what this means. GrimAge does not read a mysterious aging signal. Part of it is a methylation proxy for smoking history, which is a known risk factor. That is useful for prediction and a poor basis for assuming the number reveals "how old your cells are."
DunedinPACE: speed rather than position
Calendar age and most clock ages describe where someone is on a scale. DunedinPACE tries to measure how fast they are moving. It was derived from the Dunedin Study, a New Zealand cohort of 1,037 people born in 1972 and 1973, in which 19 biomarkers measured at four time points from age 26 to 45 were used to compute a "Pace of Aging" for each person. 5 A 173-CpG blood model was then trained to estimate that pace from a single sample. 5
The average Pace of Aging in the cohort is one biological year per calendar year with a standard deviation of 0.29, and the methylation version correlated with the 20-year measure at r = 0.78. 5 In the paper, DunedinPACE was associated with mortality in two older cohorts, with hazard ratios of 1.65 in the Framingham Offspring study and 1.26 in the Normative Aging Study. 5 Its test-retest reliability, an intraclass correlation of 0.96 in a public dataset of 36 replicate blood samples, was higher than that of its predecessor. 5
The speedometer analogy is tempting but should be used carefully. A speedometer reports a physical quantity directly. DunedinPACE reports a statistical prediction of a composite derived from 19 clinical biomarkers, in a particular birth cohort.
What "biological age" can mean
Biological age is a broad concept rather than a single measured variable. It may refer to functional capacity, physiological reserve, disease burden, molecular patterns, or predicted risk. Different measures can disagree because they sample different layers of biology. Telomere length, blood-test panels, grip strength, and a methylation clock each answer a different question.
A careful report states the clock, tissue, platform, reference population, training target, and uncertainty. Calling the output "your biological age" is understandable in public communication, but it hides the model's scope. The 12 mechanisms catalogued in the hallmarks of aging include epigenetic alteration, yet no clock has been shown to summarize all of them.
Age acceleration and residuals
Age acceleration is usually calculated as the difference between the epigenetic estimate and chronological age, or as the residual left after regressing the estimate on calendar age. A positive value means the sample looks older than expected under that model, and a negative value means it looks younger.
The residual is not a direct speedometer of aging. It can reflect cell-type composition, smoking, inflammation, medication, technical batch, tissue, population, or a model artifact. Comparing residuals across studies requires consistent processing and a shared clock. Because every clock has its own training target, the same person can receive a positive residual from one clock and a negative one from another without any error.
A worked example of how a residual is built
Imagine a research cohort of 1,000 people whose calendar ages range from 40 to 70. A clock gives each person a predicted age. Plotting predicted against actual age produces a cloud of points around a rising line, and the vertical distance of each point from that line is the residual. Someone who is 55 and scored 58 has a residual of about +3 years. Someone who is 55 and scored 52 has about -3.
Three features of this calculation matter. First, the residual is defined relative to the cohort, so it says how a person compares with the group, not how old their cells are in an absolute sense. Second, anything that moves the score without moving biology, such as a different batch of arrays or a changed blood-cell mix, lands in the residual. Third, the differences researchers care about are small next to a lifetime, and they sit in the same range as the clocks' own errors (a median of 3.6 years for Horvath's clock on held-out data) and, on some conventional clocks, the replicate noise discussed below. Researchers handle this by studying thousands of people, where random error averages out. An individual report has no such averaging.
Tissue and cell composition
Methylation differs between tissues, and blood is a mixture of immune cell types in varying proportions. If the proportions change, for example during an infection, the average methylation profile can change even when the methylation inside each cell type does not. A clock reading in blood therefore partly reflects the immune-cell lineup of that day.
Brain, liver, muscle, skin, and blood have different developmental and aging patterns. Horvath's multi-tissue design was an attempt to build one clock that works across many of them, and Hannum's blood-only clock needed adjustment elsewhere. 1 2 A saliva or cheek-swab sample contains yet another mixture, with a large share of epithelial cells. The sample source should always be reported.
Statistical deconvolution methods estimate cell proportions from reference profiles. They are themselves models and can be wrong when the reference is incomplete. Correcting for composition can remove one bias while introducing another.
Why two tests can disagree: assay and computation
Extraction, bisulfite conversion, array or sequencing platform, probe filtering, normalization, batch, storage, and sample quality all affect methylation measurements. Computational choices add more variation: probe annotation, genome build, handling of missing values, and the exact coefficient file used.
The size of this problem was quantified by Higgins-Chen and colleagues in Nature Aging in 2022. They found that technical noise produced differences of up to nine years between replicates of the same sample for six well-known clocks. 6 Retraining the clocks on principal components (summary axes that capture shared variation across many CpGs and average out probe-level noise) brought most replicates within about 1.5 years of each other. 6
That is a stark number. A change of two years in an individual's clock between visits, which would be treated as a meaningful shift in an intervention study, is smaller than the replicate spread for some conventional clocks. A public result should not be compared directly with a private consumer report unless the assay and processing are comparable.
What clocks can contribute to research
Aging trajectories
Repeated measurements let researchers study how clock estimates change within a cohort. The change may be a useful biomarker even if it is not a causal driver.
Disease and mortality association
Studies test whether clock measures are associated with disease or death, as the PhenoAge, GrimAge, and DunedinPACE papers did. 3 4 5 Association may point to a risk marker or a shared cause. It does not show that changing the clock would change the disease.
Screening interventions
An intervention study may use a clock as an intermediate biomarker, because waiting decades for mortality outcomes is impractical. The catch is that a clock change must be reproducible, biologically meaningful, and linked to outcomes people care about. See longevity interventions: what actually works for how the evidence for different interventions is graded.
Population research
Clocks can help compare molecular patterns across environments, exposures, and life stages. Studies need careful control for age, tissue, cell type, socioeconomic factors, smoking, medication, and batch.
A worked example: the thymus regeneration trial
A small study by Fahy and colleagues, published in Aging Cell in 2019, is frequently cited in popular coverage and shows both the promise and the limits of clock-based endpoints. Participants followed a one-year protocol intended to regenerate the thymus (the gland that trains T cells). The authors reported that average epigenetic age on four clocks fell by about 1.5 years from baseline, roughly 2.5 years younger than an untreated comparison group at the end, and that GrimAge dropped by about two years. 8
Several cautions apply. The trial was small, and a study of that size cannot separate a real effect from chance variation in a noisy biomarker, a point the reliability work above makes sharper. Clock change also does not prove that the participants' underlying health changed. The study illustrates why a pre-specified, adequately powered, randomized design matters more than a headline number, and why a result like this is a prompt for larger trials rather than evidence that an intervention works.
The 2.5-year gap between groups also has to be read against the measurement spread described earlier. If replicate noise on some clocks can reach several years, then a difference of that size needs repeated measurements, a defined analysis plan, and independent replication before anyone treats it as more than a signal. None of this means the result is wrong. It means a clock endpoint carries more uncertainty than the single reported figure suggests.
Causal clocks: separating damage from adaptation
A clock may predict age because the methylation changes alongside another process. The mark may be downstream of inflammation, a shift in cell composition, or a cellular response that helps rather than harms. Changing the mark experimentally might not change aging at all.
A 2024 Nature Aging study by Ying and colleagues tackled this directly. Using large genetic datasets and epigenome-wide Mendelian randomization (a method that uses naturally varying genes as stand-ins for randomized treatment), the authors identified CpG sites that may causally influence aging-related traits. Existing clocks and age-related methylation changes were not enriched at those sites. 7 They built two new clocks from the result: DamAge, which tracks harmful changes and associates with adverse outcomes including mortality, and AdaptAge, which tracks adaptive changes and associates with beneficial ones. 7
This work is still being tested by other groups, but it reframes a common assumption. A rise in methylation-based age is not automatically a sign of damage; some of it may be the body responding. The distinction is a research question, not a settled result.
Association is not causation
Predictive success does not require causal insight. A clock built from smoking-related and inflammation-related signals can predict mortality without containing any of the machinery that determines lifespan.
Causal inference requires more than a good prediction model. Researchers may use longitudinal data, genetic instruments, perturbation experiments, and triangulation with other biomarkers. Even then, conclusions remain bounded by the design of the study. For the wider debate over whether aging itself is a treatable process, see why aging is called a disease.
Consumer testing and interpretation
Commercial reports may reduce a complex model to a single age number or a score. They may not disclose the training population, tissue, coefficients, laboratory method, uncertainty, validation, or update history. A number can feel personal while remaining statistically broad.
A test can be of interest as a curiosity or research product, but a result should not be used as a diagnosis or as a reason to start medication, supplements, or extreme interventions. Health decisions require clinical context and validated tests, a theme also discussed in liquid biopsy and what blood tests can reveal.
Privacy deserves attention as well. Methylation data can reveal biological and potentially identifying information. Review storage, secondary use, deletion, sharing, and whether data may be used to train future models.
Lifestyle, environment, and clocks
Researchers examine associations between methylation patterns and exercise, smoking, diet, sleep, stress, socioeconomic conditions, pollutants, disease, and medication. The GrimAge design itself builds in smoking history, so a link between smoking and GrimAge is partly structural. 4 These relationships are complex and can be confounded: people who exercise may also differ in income, diet, and access to health care.
Intervention studies need a comparator, a pre-specified outcome, adequate duration, a reliable assay, and clinical or functional endpoints. A statistically significant clock change may not translate into a meaningful health benefit. No clock should be used to sell a guaranteed anti-aging product.
A clock-evaluation framework
| Evaluation question | Why it matters | What to report |
|---|---|---|
| What is the target? | Chronological age and outcome risk differ | Training outcome and intended use |
| Which tissue? | Methylation patterns are tissue-specific | Blood, saliva, muscle, or other source |
| Which platform? | Arrays and sequencing can differ | Laboratory method and preprocessing |
| Who was in the training data? | Population affects calibration | Age, ancestry, sex, and health context |
| What is the uncertainty? | One number can overstate precision | Error, interval, and calibration |
| Was validation independent? | Prevents overfitting | External cohort and protocol |
| How reliable is it on replicates? | Noise can swamp small changes | Test-retest statistics |
| Is there clinical utility? | Prediction is not benefit | Evidence that use improves outcomes |
This framework separates an interesting biomarker from a clinically actionable test.
Cross-cohort validation and longitudinal pitfalls
A clock that predicts age well in its training cohort can lose calibration in another. Age range, ancestry, sex, health status, medication, smoking, tissue source, and platform can all shift the input distribution. External validation should report not only a correlation but also error across relevant subgroups and whether the model systematically over- or under-estimates.
Longitudinal studies add another challenge. A person's apparent change can reflect measurement noise, cell-composition change, or a true biological shift. Repeated samples should use consistent collection and laboratory procedures, and analyses should account for regression to the mean, the tendency of an unusually high or low first reading to move toward the average on retest.
Researchers should pre-specify the clock, outcome, tissue, analysis, and handling of missing data. Reusing the same cohort to choose a clock, test an association, and report the final result can produce optimistic estimates.
Research frontiers
Newer clocks combine methylation with transcriptomics, proteomics, metabolomics, immune markers, or physiological data. Multi-omics may improve prediction but increases cost, complexity, missing data, and interpretation challenges. This is also an area where machine learning for biomarker discovery techniques are applied, along with their known risk of fitting noise.
Single-cell methylation methods may separate cell types and reveal heterogeneity, though they generate sparse data and need sophisticated analysis. Tissue- and organ-specific clocks may suit particular research questions better than one blood number. The field would benefit from shared standards, open code and coefficients, diverse cohorts, repeated measurements, and prospective validation against functional outcomes.
Common misconceptions
"The clock shows my true age." No single clock measures one accepted biological age. Each estimates its own training target, and different clocks can give different answers for the same sample.
"A younger score means I will live longer." Group-level associations exist, such as the hazard ratios reported for GrimAge and DunedinPACE. 4 5 They do not produce a precise individual lifespan prediction.
"If the number drops, the intervention worked." A score can change from noise, cell mix, or short-term physiology. Only controlled trials with clinical or functional endpoints can show benefit.
"Methylation causes aging." Most clocks were chosen for prediction rather than causation, and the 2024 causal-clock work found that existing clocks were not enriched for causally relevant sites. 7
Limitations
Epigenetic clocks are model-dependent biomarkers. Their outputs vary with tissue, cell composition, assay, sample quality, platform, processing, population, and training target. A clock estimate is not a complete biological age and does not diagnose disease, predict an individual's lifespan, or prove causation. Consumer reports may omit uncertainty and validation details. Intervention studies must show more than a change in a molecular score.
This article is biomedical education only. It is not medical advice and does not interpret a personal result or recommend a treatment, supplement, or lifestyle intervention. For urgent symptoms or an emergency, contact local emergency services.
Frequently asked questions
Q: What is an epigenetic clock? A: It is a statistical model that estimates chronological age or another age-related outcome from DNA-methylation levels at selected sites. Horvath's 2013 clock used 353 CpG sites measured across 51 tissue and cell types.
Q: Does an epigenetic clock measure true biological age? A: No single clock measures one universally accepted biological age. Horvath and Hannum trained on calendar age, PhenoAge on clinical blood markers, GrimAge on time to death, and DunedinPACE on a 20-year pace of aging, so each answers a different question.
Q: What is age acceleration, and does it prove faster aging? A: Age acceleration is the model-dependent difference or residual between an epigenetic estimate and calendar age. It does not prove faster aging, because tissue, cell composition, smoking, technical noise, and model assumptions can all shift it.
Q: Why can two tests disagree? A: They may use different clocks, tissues, platforms, coefficients, and reference populations. Technical noise alone produced differences of up to nine years between replicates of the same sample for six well-known clocks in a 2022 study.
Q: Can an epigenetic clock diagnose disease or predict my lifespan? A: No. Some clocks are associated with mortality in populations, for instance a hazard ratio of about 1.10 per year of GrimAge acceleration, but association at group level does not give a diagnosis or a precise individual prediction.
Q: Can lifestyle or treatment reverse an epigenetic clock? A: A clock score can change under some conditions, and a small 2019 trial reported lower epigenetic age after a one-year protocol. A score change does not show that underlying aging or health was reversed, and no universal personal conclusion follows from one result.
Q: Are consumer biological-age tests clinically validated? A: Validation varies widely. Check the clock, tissue, training cohort, replicate reliability, uncertainty, intended use, and data-privacy terms, and discuss any health decision with a qualified clinician.
Sources
This article is educational biomedical information and is not medical advice.
Read next:
Follow new articles
Add SciHub101 to your feed reader to see new science and technology stories.
About the Author
SciHub101 is an independent science and technology publication founded and edited by Buğra Sözeri, a software engineer and app developer based in Türkiye. AI tools assist with drafting and research. Source documentation in the existing archive is uneven, and articles are being reviewed and corrected. The Editorial Team byline identifies editorial responsibility; it does not certify specialist or independent human review. Where we compare products, anything built by our own team is labelled as such — see the editorial guidelines and About page for how corrections and disclosures work.
Related Articles

Liquid Biopsy Explained: What Blood Can Reveal About Cancer
Liquid biopsy reads tumor DNA, cells and vesicles in blood. See what ctDNA can show, where evidence is strong, and why it does not replace tissue biopsy.
Complete Biology Guide 2026 — How Life Works
The complete guide to biology in 2026: cells and genetics, evolution, the human body, neuroscience, disease, immune systems, and the future of genetic engineering.
Machine Learning for Biomarker Discovery: Finding Disease Signals in Biological Noise
AI is combing through genomic, proteomic, and metabolomic data to identify novel biomarkers—measurable biological signals that predict disease, drug response, and patient outcomes.
Horizontal Gene Transfer: How Microbes Swap DNA
Horizontal gene transfer lets microbes pass genes sideways through transformation, conjugation, and transduction, and it blurs the tree of life.
How Apoptosis Works: Why Healthy Cells Choose to Die
Apoptosis is programmed cell death. Learn how caspases, mitochondria, and Bcl-2 proteins carry it out, and what goes wrong in cancer and autoimmunity.
What Are Prions? Infectious Proteins Without DNA
Prions are misfolded proteins that spread by converting normal ones, with no DNA or RNA. How scrapie, kuru, and mad cow disease revealed the mechanism.