Neuroplasticity: The Brain's Ability to Rewire Itself Explained

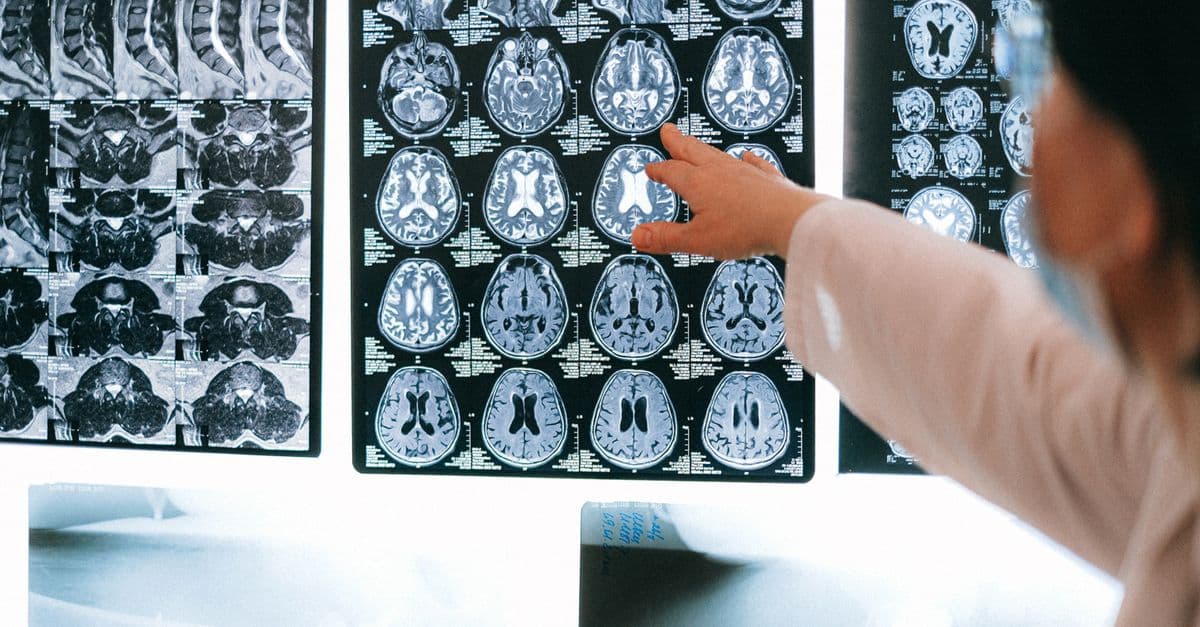
Photo: Katerina Holmes / Pexels
Neuroplasticity—the brain's remarkable ability to reorganize itself by forming new neural connections—represents one of neuroscience's most transformative insights. For centuries, scientists believed adult brains were fixed—neural circuits established in development couldn't substantially change. This dogma changed dramatically in the late twentieth century when researchers demonstrated that the adult brain retained remarkable plasticity. Experience, learning, and recovery from injury all involved structural brain reorganization. These discoveries revolutionized understanding of brain development, learning, rehabilitation, and cognitive aging. Understanding neuroplasticity explains how people recover from stroke, how musicians' brains reorganize with practice, and how chronic pain develops. This knowledge enables designing rehabilitation programs maximizing recovery potential and using neuroplasticity therapeutically.
Educational content, not medical advice. Talk to your doctor before changing any medication, treatment, or routine. Information here reflects current research but every person's situation differs.
Key Takeaways
- Adult brains retain remarkable capacity for reorganization—the old "fixed brain" dogma is false
- Experience physically reshapes brain structure through synaptic modification and circuit reorganization
- Learning involves measurable brain changes—repeated practice increases cortical representations
- Stroke recovery involves intact brain regions assuming functions of damaged areas through reorganization
- Understanding plasticity enables optimizing rehabilitation and recovering from brain injury
Background
Nineteenth-century neuroscience established that adult brains couldn't regenerate neurons. This seemed absolute—without neurogenesis, the brain couldn't reorganize. Neural circuits established during development appeared fixed. This "fixed brain" concept dominated twentieth-century neuroscience.
However, clinicians observed phenomena suggesting brain flexibility. Stroke patients sometimes recovered lost functions despite permanent neuron loss. Musicians showed brain organization differences related to expertise. These observations suggested brains weren't truly fixed.
In the 1960s-1980s, neuroscientists directly tested plasticity. Edward Taub's work with monkeys demonstrated remarkable neural reorganization following limb amputation. Additionally, improvements in neuroimaging enabled detecting brain changes accompanying learning and recovery. These advances overturned the fixed brain dogma.
The Experiment/Discovery
Sensory Cortex Reorganization (1960s-1980s): Edward Taub's experiments demonstrated that deafferenting—removing sensory input—caused dramatic sensory cortex reorganization. In monkeys with one arm immobilized, sensory cortex representing the deafferented arm was invaded by inputs from adjacent body regions. This showed that sensory cortex organization wasn't fixed but continuously reorganized based on experience.
Motor Learning and Brain Changes (1970s-present): Researchers studying motor learning discovered that practicing specific movements increased cortical representation of those movements. Musicians showed enlarged motor cortex representing fingers relative to non-musicians. This revealed that experience physically reshaped motor cortex organization.
Stroke Recovery (1980s-2000s): Neuroimaging studies of stroke patients showed remarkable recovery involving intact cortex assuming functions of damaged areas. Brain activation patterns shifted—undamaged regions increased activity compensating for damaged tissue. This reorganization enabled functional recovery despite permanent neuron loss.
Adult Neurogenesis Discovery (1998-present): Scientists discovered that neurogenesis—new neuron production—continues in adult brains, primarily in the hippocampus. This reversed the belief that adult brains couldn't generate new neurons. New neurons integrated into existing circuits, contributing to learning and memory.
The Results
These discoveries transformed understanding of brain function and potential. Rather than a fixed organ, the brain emerged as dynamic—continuously reorganizing in response to experience. This plasticity explained how people learned, recovered from injury, and adapted to environmental changes.
The findings revealed that experience literally shaped brain structure. Learning music increased auditory and motor cortex representation of sounds and movements. Learning languages increased cortex regions processing language. This experience-dependent brain reorganization explained why practice improved performance—brains were literally reorganizing to improve at practiced tasks.
Rehabilitation potential appeared far greater than previously believed. If brain regions could reassign functions, stroke recovery should be optimized through intensive practice. Physical therapy promoting intensive motor practice should trigger reorganization compensating for damage. This suggested rehabilitation strategies could maximize recovery.
The discoveries had profound implications for aging. Neuroplasticity continued throughout life. Cognitive aging wasn't inevitable deterioration but could be modified through appropriate cognitive and physical activity. Learning new skills, exercising, and cognitive challenges could maintain or improve cognitive function even in advanced age.
Impact on Medicine
Stroke Rehabilitation: Understanding that recovery involves brain reorganization transformed rehabilitation approaches. Intensive motor practice triggers reorganization of intact brain regions assuming functions of damaged tissue. Modern stroke rehabilitation emphasizes intensive, repetitive practice promoting plasticity.
Spinal Cord Injury: While complete recovery isn't possible with current treatments, understanding plasticity suggests that intensive rehabilitation might enable greater recovery than previously thought. Neuroplasticity-based rehabilitation programs show promise for improving function after spinal injury.
Phantom Limb Pain: Understanding that sensory cortex reorganization causes phantom limb pain enables developing therapies targeting the reorganized cortex. Mirror therapy exploiting plasticity shows promise for phantom pain treatment.
Cognitive Aging: Understanding that cognitive aging involves reversible changes—not irreversible deterioration—suggests interventions maintaining plasticity could prevent decline. Cognitive training, physical exercise, and social engagement maintain cognitive function through promoting plasticity.
Addiction Treatment: Addiction involves maladaptive learning—circuits encoding drug-associated memories and cravings. Understanding plasticity underlying addiction enables developing therapies using exposure, extinction learning, and environmental restructuring to reorganize addiction-related circuits.
Current Applications
Physical Rehabilitation: Post-stroke rehabilitation uses neuroplasticity principles. Intensive practice of lost functions triggers reorganization enabling functional recovery. Constraint-induced movement therapy forces use of affected limbs, promoting reorganization.
Cognitive Rehabilitation: Cognitive training following brain injury exploits plasticity for cognitive recovery. Specialized programs targeting specific cognitive deficits show modest benefits through promoting reorganization.
Musical Training: Music education exploits neuroplasticity for brain development. Musical training improves cognitive and academic performance partly through promoting plasticity-based brain reorganization.
Second Language Learning: Language learning late in life engages adult neuroplasticity. The adult brain remains capable of substantial language learning through mechanisms of neuroplasticity.
Neurofeedback: Real-time brain imaging enables neurofeedback—providing people feedback about their brain activity enabling learning to self-regulate brain function. This exploits neuroplasticity for therapeutic benefit.
Future Directions
Plasticity Enhancement: Identifying molecular mechanisms limiting adult plasticity suggests possibilities for enhancing plasticity therapeutically. Compounds that enhance growth factors or reduce inhibitory proteins might improve recovery after brain injury.
Peripheral Stimulation: Non-invasive stimulation of peripheral nerves combined with behavioral training shows promise for enhancing recovery. This approach appears to enhance neuroplasticity enabling greater functional recovery.
Pharmacological Enhancement: Medications enhancing neuroplasticity might improve rehabilitation outcomes. Compounds targeting growth factors, neurotransmitter systems, or epigenetic mechanisms show promise in preclinical studies.
Immersive Rehabilitation: Virtual reality enables intensive practice in engaging, repeatable scenarios. This might optimize neuroplasticity-based rehabilitation promoting greater functional recovery.
Personalized Neuroplasticity: Individual differences in neuroplasticity capacity suggest opportunities for personalizing rehabilitation. Identifying neuroplasticity biomarkers could optimize rehabilitation strategies for individual patients.
Molecular Mechanisms of Neuroplasticity
At the molecular level, neuroplasticity depends on activity-dependent changes in synapses—the connections between neurons. When neurons fire together repeatedly ("neurons that fire together, wire together," as Donald Hebb described), the synaptic connection strengthens. This happens through several mechanisms:
Long-term potentiation (LTP) increases synaptic strength through molecular cascades involving calcium influx, glutamate receptors, and kinase activation. Long-term depression (LTD) weakens connections through complementary mechanisms. These changes, occurring at individual synapses, underlie learning at the circuit level.
Growth factors like brain-derived neurotrophic factor (BDNF) support neuroplasticity by promoting neuron survival, growth, and synaptic formation. Exercise, cognitive challenge, and learning all increase BDNF levels, which is why these activities promote plasticity.
Source: Merzenich, M. M., et al. (1984). "Somatosensory Cortical Map Changes Following Digit Amputation in Adult Monkeys." Journal of Comparative Neurology, 224(4), 591-605.
Constraints on Neuroplasticity
While adult neuroplasticity is robust, some constraints exist. Critical periods in development involve heightened plasticity for specific functions (like language or vision). After critical periods, learning becomes possible but requires more intensive effort. The visual cortex, for example, shows heightened plasticity in early childhood when the system is calibrating to visual input. Adult plasticity for vision is reduced but not eliminated.
Some brain regions show more plasticity than others. Primary sensory cortices (vision, hearing) show less adult plasticity than association cortices or prefrontal regions involved in higher cognition. This partly reflects their specialized function—maintaining sensory representation fidelity is important and limiting plasticity helps preserve that.
Experience-Dependent Plasticity Across the Lifespan
Neuroplasticity is not uniform across the lifespan. The developing brain—particularly from infancy through adolescence—exhibits heightened plasticity, forming and refining billions of neural connections. Synaptic pruning, the removal of underutilized connections, peaks in childhood, allowing the brain to become more efficient and specialized. This is why early childhood experiences profoundly shape cognitive development, why language learning is easiest early, and why exposure to music, language, and varied sensory input during childhood produces long-lasting effects.
Critical periods represent windows of heightened plasticity for specific functions. Language acquisition shows a critical period: children exposed to language during early development acquire native-like fluency; those exposed after age 6-7 typically struggle with pronunciation and grammar. Visual development shows another critical period: a child deprived of clear visual input during early years may suffer permanent vision loss even if the eye itself heals. These periods reflect evolutionary optimization—the developing brain allocates resources to calibrating systems during windows when plasticity is cheapest (metabolically) and most consequential.
Adolescence brings a second wave of neural reorganization. The prefrontal cortex—involved in planning, decision-making, and impulse control—undergoes substantial restructuring through the teenage years into the mid-20s. This explains why adolescent learning capacity remains high even as childhood critical periods close, and why adolescence is a critical window for social and cognitive skill development.
Adult plasticity, while reduced compared to childhood, remains substantial. The adult brain continues forming new connections, reorganizing circuits, and even generating new neurons (particularly in the hippocampus, the memory center). However, adult learning typically requires more repetition and effort than childhood learning. A child can pick up a language almost effortlessly; an adult needs hundreds of hours of practice to achieve similar fluency. This doesn't mean adults can't learn—it means adult learning depends more on motivation, focused attention, and deliberate practice.
Cognitive aging brings declines in processing speed and memory, partly reflecting reduced plasticity. However, healthy aging doesn't mean inevitable cognitive decline. Cognitive engagement, physical exercise, learning new skills, and social interaction maintain plasticity throughout life. Some abilities—like crystallized intelligence (accumulated knowledge) and wisdom—improve with age. Longevity studies show that people engaging in cognitive challenges, learning new skills, and maintaining social connections show substantially slower cognitive aging than sedentary peers.
Source: Lenroot, R. K., & Giedd, J. N. (2006). "Brain development in children and adolescents: insights from anatomical magnetic resonance imaging." Neuroscience & Biobehavioral Reviews, 30(6), 718-729.
Maladaptive Plasticity: When Rewiring Goes Wrong
Not all brain reorganization produces beneficial outcomes. Maladaptive plasticity occurs when experience-driven brain changes lead to dysfunction rather than adaptation. Understanding these failures reveals how elegantly normal plasticity works.
Phantom limb pain illustrates maladaptive plasticity's consequences. After limb amputation, sensory cortex representing the missing limb doesn't simply go dormant. Instead, adjacent sensory cortex (representing other body regions) expands into the orphaned space. This remapping produces a bizarre symptom: touching the amputee's face activates cortex representing the missing limb, creating the sensation that the phantom limb is being touched. When phantom sensations include pain, the brain experiences genuine pain from stimulation of face or other body regions. This reflects the sensory cortex misinterpreting its inputs after being rewired.
Tinnitus (constant ringing in the ears) similarly reflects maladaptive plasticity. After hearing loss at specific frequencies, auditory cortex representing those frequencies reorganizes. This reorganization may produce spontaneous activation, experienced as phantom sound—tinnitus. Research shows tinnitus severity correlates with degree of cortical reorganization following hearing loss.
Chronic pain involves maladaptive plasticity in pain circuits. Normal acute pain follows tissue injury. Chronic pain persists after tissue heals because pain circuits reorganize, becoming sensitized and generating pain signals without ongoing tissue damage. Spinal cord regions receiving pain input develop increased excitability; pain-processing regions in cortex expand. The nervous system has essentially "learned" pain, and this learning persists even after the original injury heals.
Focal dystonias (involuntary muscle contractions affecting specific skilled movements) reflect maladaptive motor plasticity. Musicians and professional athletes sometimes develop dystonia affecting their craft—a violinist's fingers may involuntarily curl, or a pitcher's arm may spasm. Intensive practice, while normally promoting beneficial plasticity, appears to cause overspecialization and maladaptive rewiring of motor cortex. The affected movements involve disorganized, overlapping motor representations rather than the normal, clearly segregated representation in non-dystonics.
These maladaptive plasticity examples reveal an important principle: plasticity is experience-dependent but not inherently beneficial. The brain reorganizes based on experience, but if that experience involves injury, chronic dysfunction, or intense maladaptive practice patterns, reorganization may entrench dysfunction. Understanding these mechanisms is opening therapeutic approaches—mirror therapy for phantom pain, sound therapy for tinnitus, movement retraining for dystonias—designed to reverse maladaptive reorganization.
Source: Merzenich, M. M., Jenkins, W. M., Johnston, P., Schreiner, C., Miller, S. L., & Tallal, P. (1996). "Temporal processing deficits of language-learning impaired children ameliorated by training." Science, 271(5245), 77-81.
Neuroplasticity and Expertise: How Practice Rewires the Brain
The transition from novice to expert involves measurable brain reorganization. When someone first learns a skill—playing piano, juggling, speaking a foreign language—recruitment is broad: multiple brain regions activate, including regions not directly related to the skill. Brain imaging shows novices light up like Christmas trees, with diffuse activation across prefrontal cortex (attention), motor cortex, sensory cortex, and many other regions.
With practice, this activation becomes more efficient. Expert pianists show more focused motor cortex activation, with less activity in attention-related prefrontal regions—they don't need conscious attention for learned motor sequences. The skill has become automatic, requiring less metabolic energy and conscious effort. Motor cortex areas controlling the skilled body parts expand. String players show enlargement of cortex representing left-hand fingers (which perform complex finger movements) compared to right-hand fingers or non-musicians' hands.
Myelination contributes to expertise. White matter tracts connecting brain regions become more myelinated (wrapped in insulating myelin sheaths) with practice, increasing signal transmission speed and efficiency. Comparison of expert versus novice chess players shows greater myelination in white matter tracts supporting strategic thinking. Intensive practice literally makes neural transmission faster in skill-relevant circuits.
Synaptic density also changes. High-performing musicians and athletes show different patterns of synaptic connectivity in skill-relevant brain regions compared to novices—their neurons have formed more specialized, efficient connection patterns supporting expert performance.
The transition to expertise follows a predictable pattern. Anders Ericsson's research on deliberate practice reveals that experts typically require 10,000+ hours of focused, intentional practice to reach elite performance. This isn't arbitrary: that amount of practice is approximately what's needed to produce the neuroplastic changes supporting expert-level performance. The brain simply needs that much experience-driven reorganization to optimize circuits for expert-level skill.
Critically, not all practice is equally effective. Deliberate practice—focused, difficult, with immediate feedback and goal-directed adjustment—produces greater plasticity and faster expertise development than casual, undirected practice. Mindlessly shooting free throws produces less improvement than conscious, focused practice with deliberate attention to form and feedback. The brain reorganizes more effectively when the person is fully engaged, challenged, and actively problem-solving than during passive or automatic practice.
Source: Ericsson, K. A., Krampe, R. T., & Tesch-Römer, C. (1993). "The role of deliberate practice in the acquisition of expert performance." Psychological Review, 100(3), 363-406.
Brain-Derived Neurotrophic Factor (BDNF) and the Chemistry of Plasticity
While synaptic changes underlie neuroplasticity, molecular signals coordinate these changes. Brain-derived neurotrophic factor (BDNF) is a key player—a protein that supports the survival of existing neurons and encourages growth of new neurons and synapses. BDNF acts like neural fertilizer: cells exposed to BDNF show enhanced survival, growth, and synaptic connectivity.
BDNF levels increase with experience-dependent activity. Physical exercise dramatically increases BDNF in the hippocampus—a reason why exercise enhances memory and protects against age-related cognitive decline. Cognitive challenge and learning increase BDNF levels. Conversely, stress and depression reduce BDNF, which may explain why these conditions impair learning and memory.
The genetics of BDNF also matters. A common genetic variant (BDNF Val66Met) affects how much BDNF is released after neuronal activity. People carrying the Met allele show reduced activity-dependent BDNF release and, in some studies, reduced learning capacity compared to Val-carriers. This doesn't mean Met-carriers can't learn, but rather that they may require more practice to achieve similar expertise.
Other molecular signals support plasticity. Neurotrophic factors like nerve growth factor (NGF) and glial-derived neurotrophic factor (GDNF) support neural survival and growth. Neurotransmitter systems—particularly dopamine and acetylcholine—modulate plasticity. Dopamine release during rewarding or surprising experiences tags those experiences as important, signaling that plasticity mechanisms should strengthen related circuits. This is why reward and motivation enhance learning: the brain's neurochemistry literally shifts into learning mode.
Epigenetic mechanisms also regulate plasticity. Histone deacetylases and DNA methyltransferases can silence plasticity-supporting genes or activate them depending on experience. Environmental enrichment and learning experience upregulate histone acetylation, enhancing expression of plasticity-related genes. This reveals how experience can alter gene expression without changing DNA sequence—the same genetic blueprint supports different levels of plasticity depending on epigenetic regulation.
Understanding these mechanisms has therapeutic implications. Medications or treatments enhancing BDNF, modulating dopamine, or altering epigenetic regulation might enhance recovery from stroke or TBI, improve learning capacity, or prevent cognitive aging. Researchers are currently testing such approaches in clinical trials.
Source: Bathina, S., & Das, U. N. (2015). "Brain-derived neurotrophic factor and its clinical implications." Archives of Medical Science, 11(6), 1164-1178.
Neuroplasticity in Rehabilitation: From Theory to Practice
Understanding neuroplasticity has revolutionized rehabilitation approaches for stroke, spinal cord injury, and traumatic brain injury. Rather than accepting permanent disability as inevitable, plasticity-based rehabilitation aims to maximize functional recovery by leveraging the brain's reorganization capacity.
Constraint-induced movement therapy (CIMT) exemplifies plasticity-based rehabilitation. After stroke, patients often fall into learned non-use—they stop using the affected limb because voluntary movement is difficult, which actually prevents recovery. CIMT forces use of the affected limb (while constraining the intact limb) for intensive periods. This forced use triggers motor cortex reorganization. Patients show remarkable recovery—not because new neurons regenerate (they don't) but because remaining cortex reorganizes to support improved function. Studies show CIMT can improve motor function years after stroke when standard rehabilitation has plateaued.
Intensive repetitive practice is the core mechanism. Recovery requires thousands of high-quality repetitions of movement patterns, not passive stretching or occasional therapy sessions. Virtual reality rehabilitation, which enables engaging, highly repetitive practice in gamified scenarios, shows promise for enhancing recovery beyond conventional therapy.
Neuroimaging guidance enables monitoring reorganization during recovery. Functional MRI can reveal how brain activation patterns change with therapy—indicating whether therapy is engaging plasticity mechanisms or producing superficial movement gains without neural reorganization. This enables optimizing rehabilitation strategies for individual patients.
Timing matters. Early intensive rehabilitation produces better outcomes than delayed or less intensive therapy. The brain shows heightened plasticity in the weeks to months immediately after injury—a window when plasticity-promoting interventions may be most effective.
Rehabilitation outcomes depend not just on therapeutic intervention but on patient factors. Motivation, cognitive engagement, quality sleep, and physical fitness all support plasticity and enhance recovery. Patients who remain cognitively engaged and physically active show better recovery trajectories than those becoming depressed or sedentary. This makes neuroplasticity understanding directly applicable to maximizing individual recovery potential.
Source: Kwakkel, G., Kollen, B. J., & Krebs, H. I. (2008). "Effects of robot-assisted therapy on upper limb recovery after stroke." Neurorehabilitation and Neural Repair, 22(2), 111-121.
The Takeaway
Neuroplasticity—the brain's ability to reorganize itself through experience—represents one of neuroscience's most important discoveries. It demolished the old dogma that adult brains were fixed and unchangeable. Instead, experience continuously reshapes brain structure. Learning, recovery from injury, and even cognitive aging are fundamentally plastic processes dependent on reorganization of existing circuitry. Understanding neuroplasticity enables optimizing rehabilitation after brain injury, designing education exploiting brain learning mechanisms, and maintaining cognitive health throughout life. The brain is not a static organ but a dynamic system continuously reorganized by experience. From molecular signaling cascades involving BDNF to large-scale cortical reorganization following injury, the brain's plasticity is the foundation of human learning, adaptation, and recovery.
Frequently Asked Questions
Q: What exactly is neuroplasticity and how does it work at a cellular level?
A: Neuroplasticity is the brain's ability to reorganize itself by forming new neural connections throughout life. At the cellular level, experience strengthens frequently-used synapses (connections between neurons) through processes like long-term potentiation, where repeated activation causes calcium and signaling molecules to accumulate, making the connection more efficient. Simultaneously, unused connections weaken. This synaptic remodeling, repeated across circuits, creates structural brain changes measurable on MRI.
Q: Does the adult brain really change measurably, or is this just speculation?
A: The adult brain absolutely changes measurably. Neuroimaging studies show clear brain changes with learning and experience. Musicians' motor cortex regions controlling fingers are larger than non-musicians'. London taxi drivers, who memorize streets intensively, show enlargement of the hippocampus (memory center). Stroke patients show activation shifts in undamaged brain regions as they recover. These are not speculative; they're documented with fMRI and other neuroimaging.
Q: How long does neuroplasticity actually take to produce changes?
A: It depends on the timescale. Synaptic changes (strengthening or weakening connections) occur within hours of practice. Measurable structural changes (brain region enlargement) typically take weeks to months of consistent practice. Major reorganization after stroke, where undamaged brain regions assume functions of damaged tissue, can take months to years. The brain's reorganization operates on multiple timescales simultaneously.
Q: If adults have neuroplasticity, can I learn to be good at anything with enough practice?
A: Substantially, yes, though with caveats. Adult neuroplasticity enables learning new skills, languages, and cognitive abilities throughout life. However, younger brains show higher plasticity, so adult learning typically requires more intensive, deliberate practice. Physical constraints also matter—an adult won't become an elite gymnast through practice alone due to developmental window constraints on bone and muscle formation. But cognitive skills, languages, and most abilities remain learnable in adulthood.
Q: What's the best way to maximize neuroplasticity for learning or recovery?
A: Multiple factors promote neuroplasticity: (1) Intensive, focused practice on the skill—repetition matters. (2) Physical exercise, which increases BDNF and supports plasticity. (3) Quality sleep, which consolidates learning and enables memory integration. (4) Cognitive variety and novelty, which challenge the brain. (5) Social engagement, which supports brain health. Combining these appears more effective than any single factor alone.
Q: Can neuroplasticity actually heal brain damage, or can it only work around it?
A: Neuroplasticity enables functional recovery despite brain damage, but it works through reorganization, not healing. Dead neurons are not restored. Instead, undamaged brain regions increase their representation of functions that were lost, achieving partial functional recovery. A stroke patient recovering hand function doesn't regrow damaged tissue; rather, other motor cortex regions strengthen and assume more control. It's elegant workaround, not tissue healing.
Q: Isn't there a "critical period" for learning that makes adult learning harder or impossible?
A: Critical periods exist for certain functions (language, some aspects of vision) where development is optimized in childhood. After critical periods, learning the same skills becomes possible but typically requires more intensive, effortful practice. Adult plasticity for language learning, for example, is real but requires more practice than childhood learning. This doesn't make adult learning impossible—it makes it more effortful. The brain remains plastic throughout life.
Read next:
Follow new articles
Add SciHub101 to your feed reader to see new science and technology stories.
About the Author
SciHub101 is an independent science and technology publication founded and edited by Buğra Sözeri, a software engineer and app developer based in Türkiye. AI tools assist with drafting and research. Source documentation in the existing archive is uneven, and articles are being reviewed and corrected. The Editorial Team byline identifies editorial responsibility; it does not certify specialist or independent human review. Where we compare products, anything built by our own team is labelled as such — see the editorial guidelines and About page for how corrections and disclosures work.
Related Articles

Organ Transplantation: Christiaan Barnard's First Heart Transplant Explained
How the first human-to-human heart transplant in 1967 worked, why it nearly ended the field, and what finally made transplantation routine

mRNA Vaccines: COVID-19 Breakthrough Explained
How modified mRNA and lipid nanoparticles enabled rapid COVID-19 vaccine development, building on 30 years of foundational research by Katalin Karikó and others.
Eric Kandel's Sea Slug Memory Research Explained
How studying sea slug neurons revealed molecular mechanisms of learning and long-term memory formation
Pavlov's Classical Conditioning: Learning Theory Explained
How Ivan Pavlov's dogs revolutionized understanding of learned behavior and memory formation

How Learning Actually Works — The Science of Getting Better at Anything
Decades of cognitive science research have transformed our understanding of how brains learn. The methods most students use are among the worst. Here's what actually works.

Neuroplasticity: How the Brain Rewires Itself Throughout Life
The idea that adult brains are fixed is one of neuroscience's most consequential myths — the reality is far more remarkable and hopeful.